

 Türkçe
Ménière’s disease and vertigo are frequently confused; however, Ménière’s is only one of the diseases that causes vertigo. Vertigo is a general symptom describing the complaint of dizziness. Ménière’s, on the other hand, is an inner ear disease characterized by specific clinical findings.
Vertigo may result from many different disorders involving the brain, nervous system, or inner ear. In Ménière’s disease, vertigo is generally accompanied by tinnitus, hearing loss, and a feeling of fullness in the ear. Therefore, the differential diagnosis process is extremely important.
Ménière’s disease occurs in attacks and may last for hours, whereas the symptoms of vertigo may vary from seconds to days depending on the cause. This duration and the accompanying findings are decisive factors in diagnosis.
The treatment approach differs; while treatment targeting the underlying cause is applied in vertigo, fluid balance, dietary regulation, and medication treatment are prioritized in Ménière’s disease. Accurate diagnosis is critically important for determining the most appropriate treatment method for the patient.
| Criterion | Ménière’s Disease | Vertigo |
| Definition | A chronic disease characterized by hearing and balance disorders due to increased fluid pressure in the inner ear. | A sensation of dizziness caused by dysfunction of the balance system; it is a symptom, not a disease. |
| Causes | – Increased endolymphatic fluid pressure – Genetic predisposition – Immune system problems | – Inner ear problems (BPPV, vestibular neuritis, Ménière’s) – Central causes (stroke, migraine). |
| Symptoms | – Episodic severe dizziness – Feeling of fullness in the ear – Hearing loss, generally unilateral – Tinnitus | – Persistent or sudden dizziness – Nausea, loss of balance – Hearing loss may not be present. |
| Duration | Dizziness attacks may last between 20 minutes and several hours. | The duration of vertigo varies depending on the cause: it may last from seconds to hours. |
| Diagnostic Methods | – Audiometry – Tympanometry Vestibular tests (VNG, VEMP, v-HIT, etc.) – MRI/CT – Clinical evaluation | – Clinical examination – Positional tests (Dix-Hallpike, caloric test) – |
| Risk Factors | Stress, genetic predisposition, autoimmune diseases, QUALITY OF LIFE…. | Noise exposure, viral infections, migraine. |
| Complications | Hearing loss, social isolation, reduced quality of life | Risk of falling due to recurrent vertigo attacks and difficulty with daily activities. |
What Is Ménière’s Disease?
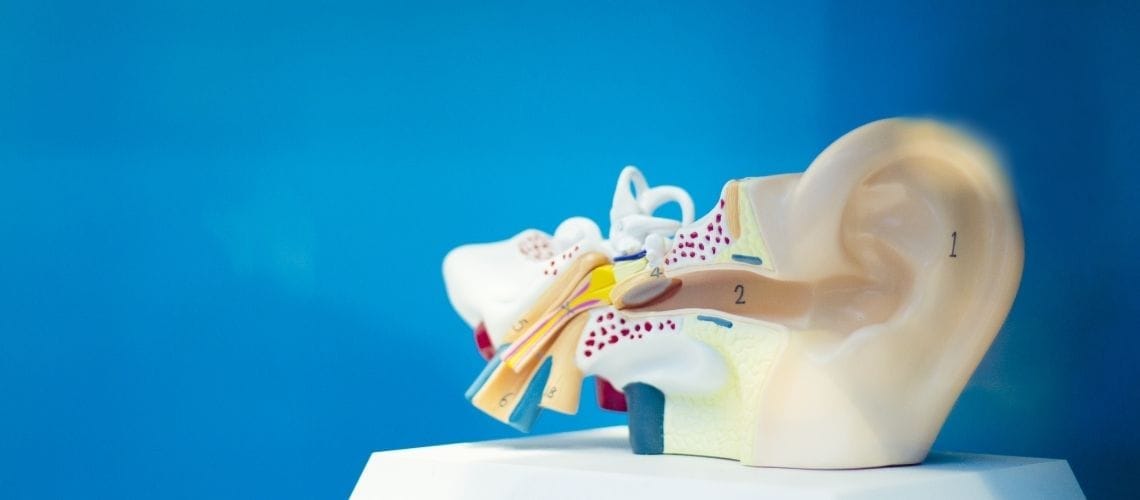
Ménière’s disease is an inner ear disorder defined by its specific symptoms. This condition presents with symptoms such as hearing loss, tinnitus, roaring sounds, and dizziness (vertigo). It generally affects one ear, and the symptoms occur episodically. Hearing loss usually begins at low frequencies and may worsen over time. Although the exact cause of Ménière’s disease is not fully known, it is associated with an abnormal increase in fluid pressure in the inner ear. This condition may result from an imbalance of the endolymphatic fluid in the inner ear.
What Are the Symptoms of Ménière’s Disease?
Ménière’s disease is generally characterized by sudden-onset severe dizziness, roaring sounds, and hearing loss. Symptoms such as nausea and vomiting may accompany it. It progresses in attacks. Hearing loss may generally improve partially or completely on its own after an attack. As the number of attacks increases, hearing loss becomes permanent. In addition, as the number of attacks increases, hypofunction also develops in the balance structures of the inner ear. Therefore, the dizziness or imbalance initially felt during the attack and for a few days afterward eventually turns into chronic imbalance. Consequently, it can be predicted that the daily activities of patients with Ménière’s disease will be affected during attacks and for several days afterward in the early stages, while their entire quality of life and working capacity may be affected once the condition becomes chronic.
Other symptoms of Ménière’s disease include:
- Ear pressure: A feeling of fullness or blockage in the ears
- Tinnitus: Persistent or intermittent ringing, buzzing, or roaring in the ears
- Fluctuating hearing loss: Hearing loss in one ear that typically affects low frequencies. Hearing loss fluctuates during attacks and becomes permanent over time
These symptoms are critically important in diagnosing Ménière’s disease and help determine appropriate treatment methods for patients.
What Are the Causes of Ménière’s Disease?
The exact cause of Ménière’s disease has not yet been fully understood. However, several factors are believed to contribute to the development of this condition:
- Genetic Predisposition: The presence of similar health problems in the families of individuals with Ménière’s disease suggests that a genetic predisposition may exist.
- Inner Ear Fluid Irregularities: Abnormal changes in the fluid pressure of the inner ear, particularly endolymphatic hydrops, are a prominent feature of Ménière’s disease.
- Autoimmune Diseases: There is evidence that certain autoimmune diseases are associated with Ménière’s disease.
- Environmental Factors: Environmental factors such as prolonged stress or exposure to certain allergens may also trigger Ménière’s disease.
Each of these factors may play a role in the development of Ménière’s disease. However, the multifactorial nature of the disease makes it difficult to determine its exact causes.
How Common Is Ménière’s Disease?
Ménière’s disease is a chronic inner ear disorder. The prevalence of Ménière’s disease varies among different sections of the population. Its annual incidence ranges from 3.5 to 513 per 100,000 people. This disease is generally more common in older age groups. It also tends to occur more frequently among women.
Some accompanying conditions associated with Ménière’s disease include:
- Migraine: The prevalence of migraine is increased among individuals diagnosed with Ménière’s disease.
- Autoimmune Diseases: Autoimmune diseases such as rheumatoid arthritis, systemic lupus erythematosus, and ankylosing spondylitis are particularly associated with this condition.
- Genetic Component: Up to 10% of cases may show familial inheritance and are associated with various genetic factors.
Distinguishing Ménière’s disease is important for accurate diagnosis and determining effective treatment methods.
Tests used to confirm the diagnosis of Ménière’s disease include:
- Pure-Tone Audiometry
- Speech Audiometry
- Immittance Assessments
- VEMP
- VNG + Caloric test
- v-HIT
- ECoG
Ménière’s is a progressive disease. Therefore, documentation is extremely important for the follow-up, treatment, and rehabilitation of Ménière’s disease.
What Are the Main Symptoms That Distinguish Ménière’s Disease from Vertigo?
First and foremost, the first thing that should be stated and understood is that VERTIGO is not a disease but a symptom. It is the Latin equivalent of the complaint of dizziness. Vertigo is a sensation of dizziness or imbalance that occurs as a result of various conditions involving the inner ear or brain.
Ménière’s disease, on the other hand, is a disease characterized by attacks of dizziness. Ménière’s disease is a chronic inner ear disorder characterized by vertigo, tinnitus, a feeling of fullness in the ear, and fluctuating hearing loss. Ménière’s generally affects one ear. Although rare, it may affect both ears.
While Ménière’s disease includes additional auditory symptoms such as tinnitus, hearing loss, and ear fullness together with vertigo, vertigo alone does not include these specific ear-related problems.
How Common Is Hearing Loss in Ménière’s Disease?
The prevalence of Ménière’s disease varies worldwide and ranges from 3.5 to 513 per 100,000 people. In the United States, approximately 0.2% of the population is affected, corresponding to about 615,000 people, and 45,500 new cases are diagnosed each year. The disease generally occurs between the ages of 40 and 60 and is slightly more common in women than in men. Involvement of both ears occurs in approximately 15% of cases. Ménière’s disease is characterized by dizziness, tinnitus, and a feeling of fullness in the ear. Hearing loss may fluctuate in the early stages and may become permanent over time. Some studies indicate that hearing loss is observed in approximately 90% of cases. Which tests are used in the diagnosis of vertigo and Ménière’s disease?
Ménière’s disease is diagnosed through clinical evaluations and various tests. Documentation is an essential prerequisite before a diagnosis of Ménière’s disease can be made.
Symptoms include attacks of dizziness, hearing loss, tinnitus, and a feeling of fullness in the ear. Hearing tests are performed to determine hearing loss, and loss is generally observed at low and middle frequencies. Electrocochleography (ECoG) helps detect endolymphatic hydrops by measuring inner ear fluid pressure. However, it is not frequently preferred because of difficulties in application and analysis. Tests performed with videonystagmography (VNG) are among the most frequently preferred methods. VNG is a special device equipped with infrared cameras that enables eye movements to be recorded and analyzed. Each of the tests performed examines pathways involved in balance control. The results help determine whether the cause of the patient’s dizziness originates from the vestibular system or is related to the central nervous system. Within this framework, the caloric test is one of the most important tests that should be performed in the diagnosis of Ménière’s disease. The caloric test is based on heating and cooling the inner ear using air or fluid. Eye movements caused by this stimulation are recorded and analyzed. VEMP must be used in the diagnosis of Ménière’s disease to evaluate otolith functions. c-VEMP, performed by recording particularly from the neck region, the SCM muscle, is highly valuable for diagnosing Ménière’s disease. Tests used to evaluate hearing should not be limited to pure-tone audiometry; immittance assessments and acoustic reflex responses must also be documented. Although the glycerol test, which was used more frequently in the past, is still occasionally preferred, it is now used less often due to various application difficulties. In addition, MRI performed using certain specialized techniques provides important information about hydrops. Screening MRI or CT is used to exclude other diseases that present with similar symptoms.
How Do the Treatment Methods for Ménière’s Disease and Other Conditions Accompanied by Vertigo Differ?
The treatment methods for Ménière’s disease and other conditions causing vertigo differ depending on the underlying causes. Ménière’s disease has a stepwise treatment protocol consisting of a low-salt diet, medical treatments, and surgical procedures.
On the other hand, the most common condition accompanied by vertigo and responsible for vertigo being mistaken for a disease is BPPV, commonly known as displaced ear crystals. BPPV is a mechanical disorder. It is treated with the appropriate maneuver according to its variant.
Other conditions causing vertigo, such as neuritis and labyrinthitis, require both medical treatment and vestibular rehabilitation. In conditions such as vestibular migraine, the migraine component is controlled by neurologists, while vestibular rehabilitation and lifestyle modifications are essential for improving the person’s balance control and helping them manage their attacks.
How Important Are Lifestyle Changes for Individuals with Ménière’s Disease?
Lifestyle changes for Ménière’s disease are generally recommended, including reducing salt intake, increasing water consumption, and sleeping in darkness. However, a Cochrane review found that the evidence supporting the effectiveness of these interventions was highly uncertain; the only two small studies included lacked robust data on important outcomes such as the frequency and severity of dizziness.
Frequently Asked Questions
Ménière’s disease is one of the inner ear diseases that causes vertigo. Vertigo is not a disease but a symptom in which the person feels that they or their surroundings are spinning. Therefore, not every case of vertigo means Ménière’s disease.
In Ménière’s disease, vertigo is accompanied by tinnitus, a feeling of fullness in the ear, and fluctuating hearing loss. In other types of vertigo, these symptoms may not always occur, and the underlying cause may be different.
In Ménière’s disease, vertigo attacks generally last between 20 minutes and several hours. In other causes of vertigo, such as BPPV, dizziness usually occurs as brief attacks that end within seconds.
The patient’s history, ear, nose, and throat examination, audiological evaluation, and hearing tests are highly important in diagnosis. When necessary, v-HIT, VEMP, VNG, and imaging methods may also be used in differential diagnosis.
The treatment of vertigo varies according to the underlying cause. In Ménière’s disease, medication treatment, a low-salt diet, and follow-up are prioritized, while positional maneuvers may be applied in BPPV and different treatment methods may be used for other vestibular disorders.
Vestibular rehabilitation may be beneficial for imbalance that develops after Ménière’s disease and in many vestibular disorders. A personalized exercise program prepared by an audiologist supports the adaptation of the balance system.
Fluctuating hearing loss is one of the characteristic features of Ménière’s disease. Hearing is generally not affected in common causes of vertigo such as BPPV. This difference is one of the important clues in differential diagnosis.
A low-sodium diet, regular sleep, and stress management may be recommended for patients with Ménière’s disease. In other types of vertigo, treatment targets the cause, and lifestyle recommendations are shaped according to the underlying condition.
If dizziness is accompanied by sudden hearing loss, speech impairment, double vision, severe headache, altered consciousness, or weakness in the arms or legs, emergency medical evaluation should be performed. These symptoms may suggest different conditions.
People experiencing recurrent dizziness, tinnitus, hearing loss, or imbalance should consult an audiologist and an ear, nose, and throat specialist without delay. Early evaluation is important for accurate diagnosis and an effective treatment plan.

Dr. Audiologist Emel Uğur was born in 1982 in Çanakkale. She specialized in Pediatric Audiology, Otologic Disorders, and Vestibular System Disorders, and served for 15 years at the Istanbul Training and Research Hospital. In 2015, she joined the Acıbadem Healthcare Group. She currently works as an Audiologist at the Acıbadem Altunizade Hospital and also serves as a faculty member and program director in the Acıbadem University Vocational School of Health Services Audiometry Program.









Location of our clinic in Istanbul, Turkey